Peripheral Artery Disease (PAD): Recognizing the Warning Signs in Your Legs
Peripheral Artery Disease (PAD) is a common yet frequently overlooked circulatory condition in which narrowed arteries reduce blood flow to the limbs. While the condition can affect various parts of the body, it most predominantly manifests in the legs. From a clinical perspective, PAD is a manifestation of systemic atherosclerosis, where the accumulation of lipid-rich plaque within the arterial walls leads to stenosis, or narrowing, of the vessel lumen. This restriction impedes the delivery of oxygenated blood to the distal extremities, resulting in a spectrum of symptoms that range from mild discomfort to severe tissue damage.
Recognizing the warning signs of PAD is critical for preventing progression to critical limb ischemia and preserving limb viability. Colorado Cardiovascular Surgical Associates (CCVSA) emphasizes the importance of understanding these symptoms, as early intervention significantly improves long-term outcomes. By identifying the physiological cues the body provides, patients can seek appropriate vascular evaluation and management strategies.
The Physiology of Arterial Insufficiency
To understand the symptoms of PAD, one must first understand the pathophysiology of arterial insufficiency. The peripheral arteries are responsible for transporting oxygen and nutrients to the muscles and skin of the legs. When atherosclerosis occurs, plaque composed of fat, cholesterol, calcium, and other substances found in the blood builds up inside the arteries. Over time, this plaque hardens and narrows the arteries, limiting the flow of oxygen-rich blood to the organs and other parts of the body.
During periods of rest, the narrowed vessels may still provide adequate blood flow to meet the metabolic demands of the muscle tissue. However, during physical activity, the metabolic demand for oxygen increases. If the arteries are stenosed, they cannot vasodilate sufficiently to increase blood flow, leading to ischemia (a shortage of oxygen) in the muscle tissue. This ischemic state triggers pain signals, acting as a biological warning system that the tissue is compromised. For more detailed information on this condition, reviewing resources on Peripheral Arterial Disease can provide a deeper understanding of the disease process.
Intermittent Claudication: The Hallmark Symptom
The most classic symptom associated with PAD is intermittent claudication. This clinical term refers to muscle pain or cramping in the legs that is triggered by activity, such as walking, and is consistently relieved by a few minutes of rest. The pain is reproducible; a patient may find they can walk a specific distance—perhaps two blocks—before the pain necessitates a halt. Once the metabolic demand of the muscles decreases during rest, the pain subsides, only to return upon resumption of activity.
The location of the pain often correlates with the location of the arterial blockage:
- Buttock and Hip Pain: Suggests blockages in the aorta or iliac arteries (the main arteries in the pelvis).
- Thigh Pain: Indicates potential occlusion in the femoral artery.
- Calf Pain: This is the most common presentation and typically points to blockages in the superficial femoral or popliteal arteries.
- Foot Pain: Suggests disease in the tibial or peroneal arteries of the lower leg.
It is important not to dismiss these symptoms as merely a sign of aging or general fatigue. Unlike joint pain caused by arthritis, which may persist at rest or fluctuate with weather changes, claudication is specifically tied to exertion. Patients experiencing these specific mobility challenges should consult with a specialist. You can learn more about general circulation issues in the article Peripheral Artery Disease (PAD) & Poor Circulation: What You Need To Know.
Critical Limb Ischemia and Advanced Symptoms
If left untreated, PAD can progress to a more severe stage known as Critical Limb Ischemia (CLI). At this stage, the blood flow is so severely compromised that the metabolic needs of the tissue are not met even at rest. This represents a significant threat to the viability of the limb and requires urgent vascular attention.
Warning signs of advanced PAD and CLI include:
Ischemic Rest Pain
Unlike claudication, rest pain occurs when the patient is sedentary, often striking at night when the legs are elevated in bed. Gravity no longer assists blood flow to the feet, causing severe burning or aching pain in the toes or forefoot. Patients often report dangling their legs over the side of the bed or sleeping in a chair to find relief, as this allows gravity to assist arterial perfusion.
Dermatological Changes
Vascular surgeons look for specific physical signs on the legs and feet that indicate chronic poor circulation. These include:
- Skin Discoloration: The skin may appear pale or blanched when the leg is elevated and turn deep red or purple (rubor) when dependent (hanging down).
- Trophic Changes: The skin may become thin, brittle, and shiny. There is often a noticeable loss of hair on the lower legs and toes.
- Temperature Asymmetry: One leg or foot may feel significantly cooler to the touch compared to the other, or compared to the rest of the body.
- Nail Changes: Toenails may become thickened, opaque, and slow-growing due to lack of nutrients.
For a checklist of physical indicators, refer to 5 Warning Signs of Poor Circulation You Shouldn’t Ignore.
Non-Healing Wounds
Perhaps the most alarming sign of advanced PAD is the presence of arterial ulcers. These sores typically form on the toes, feet, or heels and are characterized by a “punched-out” appearance. Unlike venous ulcers, which are often wet and located near the ankle, arterial ulcers are often dry, painful, and exhibit little to no healing over time. The lack of blood flow prevents the immune system and repair cells from reaching the injury site. If you notice wounds that do not heal, seeking care from expert vascular services is imperative to prevent infection and gangrene.
Differentiating PAD from Other Conditions
Accurately diagnosing PAD involves distinguishing it from other conditions that cause leg pain. For instance, spinal stenosis or sciatica can cause pain that radiates down the leg, but this “pseudoclaudication” often relates to posture (standing vs. sitting) rather than solely the hemodynamic demand of exercise. Similarly, venous insufficiency affects the return of blood to the heart rather than the supply to the legs. Understanding the difference between arterial and venous issues is vital; for example, distinguishing varicose veins vs. spider veins involves different pathology than arterial blockages.
Furthermore, conditions like deep vein thrombosis (DVT) present with swelling and acute pain, contrasting with the chronic, exercise-induced nature of PAD. Information on preventing venous clots can be found in the guide: Tips for Preventing Deep Vein Thrombosis.
Risk Factors and Comorbidities
Understanding who is at risk aids in early detection. The risk factors for PAD mirror those of coronary artery disease and cerebrovascular disease. Smoking is the single most significant modifiable risk factor; it accelerates plaque formation and damages the endothelium (inner lining) of the blood vessels. Diabetes Mellitus is another major contributor. High blood sugar levels damage blood vessels over time and can also cause neuropathy (nerve damage), which may mask the pain of claudication or foot injuries.
Other risk factors include:
- Hypertension (High Blood Pressure)
- Hyperlipidemia (High Cholesterol)
- Advanced Age (risk increases significantly after age 50)
- Family history of vascular disease
Because atherosclerosis is a systemic disease, patients with PAD are also at higher risk for heart attack and stroke. It is not uncommon for a patient with leg symptoms to also require evaluation for Carotid Artery Disease or Abdominal Aortic Aneurysms. Managing systemic health is crucial, particularly for diabetic patients, as detailed in April is Defeat Diabetes Month: Learn How Diabetes Impacts Vascular Health.
Diagnostic Evaluation
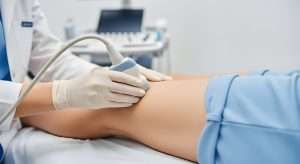
When warning signs are identified, vascular specialists utilize non-invasive testing to confirm the diagnosis. The Ankle-Brachial Index (ABI) is the primary screening tool. It compares the blood pressure in the ankle with the blood pressure in the arm. An ABI ratio of 0.9 or lower is generally diagnostic of PAD. Further imaging, such as duplex ultrasound, CT angiography, or magnetic resonance angiography (MRA), allows surgeons to visualize the anatomy of the blockage and plan potential interventions.
Early screening is recommended for high-risk individuals. Information regarding diagnostic appointments can be found at CCVSA Screenings.
Treatment Pathways
The management of Peripheral Artery Disease is multifaceted, focusing on symptom relief and cardiovascular risk reduction. Conservative management includes smoking cessation, antiplatelet therapy, lipid management, and structured exercise programs designed to improve walking distance by promoting collateral circulation.
When conservative measures are insufficient, or in cases of critical limb ischemia, revascularization becomes necessary. Modern vascular surgery offers a range of options:
- Endovascular Therapy: These are minimally invasive vascular procedures where a catheter is threaded through the vessels to the site of the blockage. Techniques such as balloon angioplasty (stretching the artery) and stenting (placing a mesh tube to keep the artery open) are commonly employed.
- Surgical Bypass: In cases of long-segment disease or when endovascular options are not feasible, a surgical bypass may be performed. This involves using a vein from the patient’s body or a synthetic graft to create a detour around the blocked artery, restoring direct blood flow to the lower limb.
Decisions regarding the most appropriate intervention are made by board-certified vascular surgeons, such as Dr. Marcus R. Kret or Dr. Colleen S. Hupp, who evaluate the specific anatomical and physiological needs of each patient.
Expert Vascular Care in Colorado
Recognizing the warning signs of PAD—from the initial onset of claudication to the more severe presentation of rest pain—is the first step toward vascular health. Lower extremity pain should never be ignored, particularly in individuals with risk factors for atherosclerosis. Timely evaluation by a vascular specialist ensures that patients receive a comprehensive care plan tailored to preserving limb function and improving quality of life.
Colorado Cardiovascular Surgical Associates delivers expert vascular, thoracic, and cardiac care through an all–board‑certified physician team—each specializing in their field—ensuring you receive the highest level of surgical expertise. With multiple convenient locations across Colorado—including Englewood, Aurora, and Frisco—and access to advanced diagnostics, minimally invasive procedures, and dedicated 24/7 surgeon availability, CCVSA offers comprehensive, compassionate care tailored to each patient. Their focus on state‑of‑the‑art technology and personalized treatment pathways helps patients achieve faster recovery and peace of mind when it matters most.
For more information or to schedule a consultation with one of our trusted surgeons, please contact CCVSA or visit our Englewood, Aurora, or Lakewood/Frisco locations. You can also stay connected with CCVSA on Facebook and Instagram.