Mesenteric Ischemia: Identifying “Stomach Pain” Caused by Poor Blood Flow
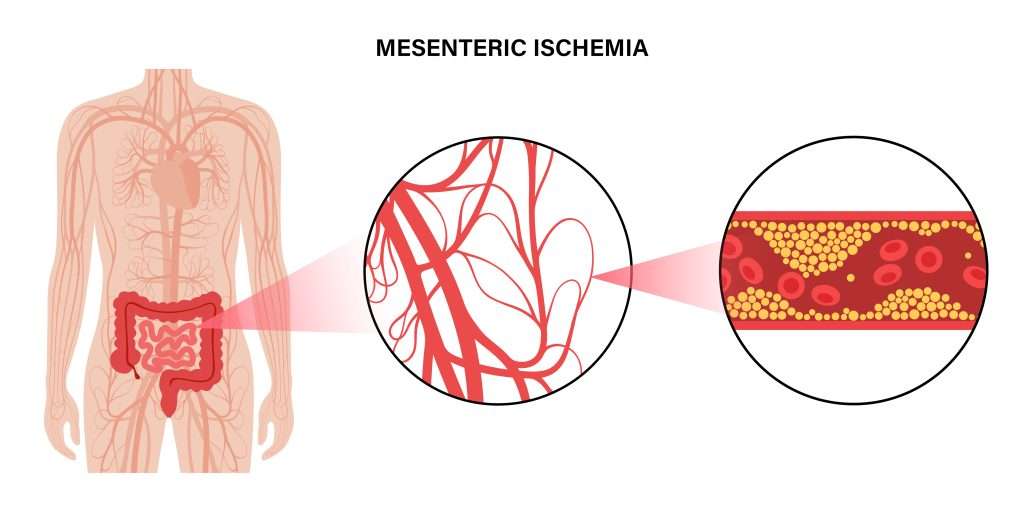
Abdominal pain is a nonspecific symptom often attributed to gastrointestinal issues such as gastritis, acid reflux, or gallstones. However, when abdominal pain correlates specifically with eating and is accompanied by unintended weight loss, it may signal a vascular condition known as mesenteric ischemia. This condition results from restricted blood flow to the small intestine, large intestine, or stomach. Much like the heart requires adequate blood flow to function, the digestive organs rely on a robust vascular supply, particularly during the digestion process.
For patients and medical providers alike, recognizing the distinction between common gastric ailments and vascular insufficiency is critical. Mesenteric ischemia is effectively “angina of the gut.” At Colorado Cardiovascular Surgical Associates (CCVSA), the focus remains on early detection and intervention to restore blood flow, alleviate pain, and prevent irreversible damage to the intestinal tract.
The Physiology of Mesenteric Circulation
To understand mesenteric ischemia, one must understand the anatomy of the abdominal aorta and its branches. Three main arteries supply blood to the digestive organs: the celiac artery, the superior mesenteric artery (SMA), and the inferior mesenteric artery (IMA). These vessels provide the oxygen and nutrients necessary for the intestines to perform peristalsis and absorption.
After a meal, the metabolic demand of the intestines increases significantly. In a healthy vascular system, the arteries dilate to accommodate this increased blood flow. However, in the presence of vascular disease, such as atherosclerosis (hardening of the arteries), these vessels may be narrowed or blocked. When the demand for blood flow exceeds the supply during digestion, the resulting ischemia causes severe pain. This mechanism is physiologically identical to chest pain caused by coronary artery disease.
Classifying Mesenteric Ischemia
Mesenteric ischemia presents in two distinct forms: chronic and acute. The clinical approach, urgency, and treatment pathways differ significantly between the two.
Chronic Mesenteric Ischemia (CMI)
Chronic mesenteric ischemia is a progressive condition, typically caused by the gradual buildup of plaque (atherosclerosis) within the mesenteric arteries. This process is similar to the pathology observed in Peripheral Arterial Disease (PAD), where plaque restricts flow to the legs. In CMI, collateral blood vessels may form over time to compensate for the blockage, but eventually, these collaterals become insufficient to meet the metabolic demands of digestion.
The hallmark symptom of CMI is postprandial abdominal pain—severe cramping occurring 15 to 30 minutes after eating and lasting for several hours. This pain leads to a conditioned response known as “food fear” (sitophobia), where patients reduce their food intake to avoid pain, resulting in significant weight loss.
Acute Mesenteric Ischemia (AMI)
Acute mesenteric ischemia is a medical emergency characterized by the sudden and complete blockage of blood flow to a portion of the intestine. This is frequently caused by an embolus (blood clot) traveling from the heart or aorta to the mesenteric arteries. Without immediate restoration of blood flow, intestinal tissue can become necrotic (die) within hours. Symptoms typically include the sudden onset of severe abdominal pain that seems disproportionate to physical exam findings.
Risk Factors and Etiology
The primary driver of chronic mesenteric ischemia is atherosclerosis. Therefore, the risk factors for CMI mirror those of other cardiovascular conditions. Individuals with a history of smoking, hypertension, hyperlipidemia (high cholesterol), and diabetes are at elevated risk. Furthermore, patients who have already been diagnosed with vascular issues elsewhere in the body, such as carotid artery disease or coronary artery disease, have a higher probability of developing mesenteric, renal, or peripheral vascular issues.
Age is also a contributing factor, as vascular elasticity decreases and plaque burden increases over time. Understanding these risk factors is essential for preventive care for cardiovascular health. Early management of cholesterol levels and blood pressure can slow the progression of atherosclerotic plaque.
Diagnostic Pathways
Diagnosing mesenteric ischemia requires a high index of suspicion, as the symptoms often mimic other intra-abdominal pathologies. A thorough patient history focusing on the timing of pain relative to meals and weight history is the first step. When a vascular cause is suspected, specialized imaging is employed.
Duplex ultrasound is a non-invasive screening tool used to assess blood flow velocity in the mesenteric arteries. High velocities often indicate narrowing (stenosis). For a more detailed anatomical map, a Computed Tomography Angiogram (CTA) is the gold standard. A CTA provides high-resolution images of the aorta and its branches, allowing vascular surgeons to pinpoint the location and severity of the blockage. Additionally, detecting potential comorbidities, such as an abdominal aortic aneurysm, is often part of the comprehensive evaluation during these scans.
Treatment and Revascularization
The primary goal of treating mesenteric ischemia is revascularization—restoring adequate blood flow to the intestines to relieve symptoms and prevent tissue death. The choice of procedure depends on the patient’s anatomy, overall health, and the severity of the disease. Board-certified vascular surgeons, such as Dr. Marcus R. Kret and Dr. Colleen S. Hupp, evaluate each case to determine the most appropriate intervention.
Endovascular Therapy
Endovascular therapy is a minimally invasive vascular procedure often used as the first line of treatment for chronic mesenteric ischemia. This approach involves accessing the arterial system through a small puncture in the groin or arm. A catheter is guided to the narrowed mesenteric artery, where balloon angioplasty and stenting are performed to widen the vessel and maintain patency.
The benefits of endovascular approaches include shorter hospital stays, reduced recovery times, and lower perioperative risks compared to open surgery. This is particularly beneficial for elderly patients or those with significant comorbidities.
Open Surgical Bypass
In cases where the blockage is extensive, calcified, or not amenable to stenting, open surgical revascularization may be required. This involves creating a bypass graft—using either a synthetic tube or a vein from the patient’s body—to route blood flow around the blocked section of the artery. While this is a more invasive procedure, it has proven durability and remains a vital option in the vascular surgeon’s armamentarium.
The expertise required for these complex procedures underscores the importance of seeking care from dedicated specialists. Understanding the role of a vascular surgeon ensures that patients receive a comprehensive evaluation of all potential treatment modalities.
The Importance of Comprehensive Vascular Care
Vascular health is systemic. A patient presenting with mesenteric ischemia may also have undiagnosed issues in other vascular beds. For instance, Peripheral Artery Disease (PAD) frequently co-exists with mesenteric disease. Identifying these interconnected conditions allows for a holistic treatment plan that addresses the patient’s overall longevity and quality of life.
Regular screenings and follow-up appointments are vital for monitoring the progression of vascular disease. Whether a patient is seen at the Englewood location or by vascular surgeons in Aurora, CO, the continuity of care remains a priority. Managing underlying conditions such as diabetes is also crucial, as detailed in resources regarding how diabetes impacts vascular health.
Expert Vascular Care for Colorado
Colorado Cardiovascular Surgical Associates (CCVSA) has been a trusted provider of vascular surgery in the Denver area for over 27 years. Serving the community since 1996, CCVSA delivers expert vascular, thoracic, and cardiac care through an all–board‑certified physician team. Each physician, including Dr. Samuel Victoria, Dr. Srikant Sivaraman, and Dr. Danielle Sethi, specializes in their field, ensuring patients receive the highest level of surgical expertise.
With multiple convenient locations including Aurora, Englewood, Lone Tree, Westminster, Lakewood, and Frisco, and access to advanced diagnostics and minimally invasive procedures, CCVSA offers comprehensive, compassionate care tailored to each patient. The practice provides dedicated 24/7 surgeon availability, emphasizing accessibility, dependability, and patients’ rights. Their focus on state‑of‑the‑art technology and personalized treatment pathways helps patients achieve faster recovery and peace of mind when it matters most. Recognized as some of Denver’s top doctors by 5280 Magazine, CCVSA works closely with primary care physicians to ensure a smooth referral process and optimal healthcare outcomes.
Connect with Colorado Cardiovascular Surgical Associates on social media: Facebook, Instagram, and find their locations on Google Maps: Location 1, Location 2, and Location 3.