Fenestrated EVAR (FEVAR): Custom-Built Solutions for Complex Aortic Aneurysms
The landscape of vascular surgery has evolved significantly over the past two decades, particularly in the treatment of aortic pathology. An abdominal aortic aneurysm (AAA) represents a potentially life-threatening condition where the aorta—the largest artery in the body—weakens and bulges. While traditional open surgery was once the only option, endovascular aneurysm repair (EVAR) has become the standard for many patients. However, standard EVAR is not suitable for everyone. For patients with complex anatomy, particularly where the aneurysm extends near or involves the arteries supplying the kidneys and other visceral organs, a specialized approach known as Fenestrated EVAR (FEVAR) provides a life-saving, minimally invasive solution.
The Anatomical Challenge of Complex Aneurysms
To understand the necessity of FEVAR, one must first understand the limitations of standard endovascular repair. A standard stent-graft is a fabric-covered metal mesh tube used to reinforce the aorta. To function correctly, this graft requires a “landing zone” or “neck”—a segment of healthy aorta both above and below the aneurysm where the graft can seal tightly against the arterial wall. This seal prevents blood from continuing to fill the aneurysm sac.
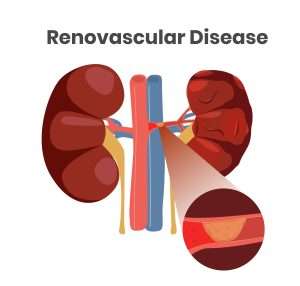
In approximately 10% to 15% of AAA cases, the aneurysm begins immediately below, or extends up to, the renal arteries (which supply blood to the kidneys). These are classified as juxtarenal or pararenal aneurysms. In such cases, placing a standard stent-graft would cover the openings of the renal arteries, effectively cutting off blood flow to the kidneys and causing immediate renal failure. Historically, these patients required open surgical repair, a major procedure involving a large abdominal incision and significant recovery time.
Defining Fenestrated EVAR (FEVAR)
Fenestrated Endovascular Aneurysm Repair (FEVAR) is a sophisticated evolution of the standard EVAR technique. The term “fenestrated” is derived from the Latin word for window. These grafts are custom-engineered with precise holes (fenestrations) or cut-outs that align perfectly with the patient’s specific anatomy. These fenestrations allow the graft to be placed across the renal and visceral arteries to achieve a seal in healthy tissue higher up in the aorta, while still preserving blood flow to critical organs through the reinforced windows.
This technology extends the benefits of minimally invasive vascular procedures to a broader patient population who were previously deemed ineligible for standard stenting. By utilizing FEVAR, surgeons can treat complex aneurysms without the physiological stress associated with open thoracic-abdominal surgery.
The Customization and Manufacturing Process
Unlike off-the-shelf stent grafts used in standard EVAR, a fenestrated graft is patient-specific. The process begins with high-resolution computed tomography (CT) angiography. This imaging is critical for mapping the exact geometry of the patient’s aorta and the precise location of the renal arteries, the superior mesenteric artery (supplying the intestines), and the celiac trunk.
Vascular surgeons, such as Dr. Marcus R. Kret or Dr. Colleen S. Hupp, work in conjunction with engineering teams to design the graft. The position of every fenestration is calculated to the millimeter. Due to the high level of customization required, there is typically a manufacturing lead time of several weeks. During this waiting period, blood pressure management and monitoring are essential to prevent aneurysm rupture before the device is ready.
The FEVAR Procedure
The implantation of a fenestrated graft is a technically demanding procedure that should only be performed by experienced, board-certified vascular surgeons at a center of excellence. The surgery typically involves the following steps:
Access and Delivery
Similar to standard EVAR, the procedure is performed through small incisions or punctures in the femoral arteries at the groin. Catheters and guidewires are navigated through the iliac arteries up into the aorta under fluoroscopic (X-ray) guidance.
Graft Deployment and Cannulation
This is the most critical phase. The main body of the fenestrated graft is partially deployed. The surgeon must manipulate the device to ensure the fenestrations align perfectly with the target arteries. Once alignment is confirmed via angiography, the surgeon passes smaller, covered stents through the graft’s fenestrations and into the renal and visceral arteries. This creates a secure channel for blood flow into the organs while sealing the aneurysm off from systemic blood pressure.
Completion
Once all fenestrations are stented and the main graft body is fully expanded, the delivery systems are removed. The result is a continuous pipeline that excludes the aneurysm while maintaining patent pathways to the kidneys and digestive organs.
Advantages Over Open Repair
For patients with significant comorbidities, such as heart disease, peripheral arterial disease (PAD), or respiratory issues, FEVAR offers distinct advantages over open surgery:
- Reduced Trauma: FEVAR avoids the need for a large abdominal or thoracoabdominal incision, reducing post-operative pain and the risk of wound complications.
- Shorter Hospital Stay: Patients undergoing FEVAR typically spend fewer days in the hospital compared to open repair recipients, often returning home within 2 to 4 days.
- Faster Recovery: The return to normal daily activities is significantly accelerated, allowing patients to maintain their quality of life.
- Lower Mortality and Morbidity: Studies indicate that for high-risk patients, endovascular approaches carry lower perioperative mortality rates compared to open surgery.
Patient Eligibility and Screening
Not every patient with a complex aneurysm is a candidate for FEVAR. Anatomical suitability is determined through rigorous vascular screenings and imaging. Factors influencing eligibility include the quality of the femoral and iliac arteries (access vessels), the angulation of the aorta, and the condition of the target renal and visceral arteries. Severe calcification or tortuosity (twisting) of the arteries can make the delivery of the device difficult or impossible.
Furthermore, because the procedure involves the use of iodine-based contrast dye and catheter manipulation near the kidneys, patients must have adequate renal function. The vascular team evaluates each case individually to determine if FEVAR, open surgery, or medical management is the safest path forward.
Risks and Considerations
While minimally invasive, FEVAR is a major vascular intervention carrying specific risks. Potential complications can include:
- Endoleak: Blood flow may persist outside the graft but within the aneurysm sac. While some leaks resolve spontaneously, others may require secondary interventions.
- Renal Function Decline: Manipulation of the renal arteries or contrast toxicity can impact kidney function.
- Access Site Issues: Hematoma or injury to the femoral arteries where the catheters were inserted.
- Spinal Cord Ischemia: In extensive repairs, blood supply to the spinal cord can be affected, though protocols are in place to monitor and mitigate this risk.
Patients are encouraged to review these considerations in detail with their provider. Resources such as educational articles and direct consultations help clarify the risk-benefit ratio for each individual.
Post-Operative Surveillance
Successful implantation is not the end of the treatment pathway. Lifelong surveillance is mandatory for all patients undergoing endovascular aortic repair. This ensures the graft remains in the correct position, the stents remain patent (open), and the aneurysm sac shrinks over time. Follow-up protocols typically involve CT scans and ultrasound imaging at one month, six months, and annually thereafter.
This commitment to long-term care allows the surgical team to detect and address any late complications, such as endoleaks or device migration, before they become symptomatic. Patient resources and clear communication channels ensure that individuals remain engaged in their long-term vascular health.
Why Expertise Matters
FEVAR is among the most complex procedures in the field of vascular surgery. It requires a high level of technical skill, advanced imaging capabilities, and a multidisciplinary team approach. Selecting a practice with board-certified vascular surgeons who perform these procedures regularly is crucial for optimal outcomes.
Surgeons such as Dr. Samuel Victoria and Dr. Danielle Sethi, alongside their colleagues, represent the level of specialized training required to handle complex aortic pathologies. A dedicated team ensures that from the initial abdominal aortic aneurysm diagnosis to post-operative recovery, every aspect of care is managed with precision.
About Colorado Cardiovascular Surgical Associates
Colorado Cardiovascular Surgical Associates (CCVSA) delivers expert vascular, thoracic, and cardiac care through an all–board‑certified physician team—each specializing in their field—ensuring you receive the highest level of surgical expertise. With multiple convenient locations across Colorado and access to advanced diagnostics, minimally invasive procedures, and dedicated 24/7 surgeon availability, CCVSA offers comprehensive, compassionate care tailored to each patient. Their focus on state‑of‑the‑art technology and personalized treatment pathways helps patients achieve faster recovery and peace of mind when it matters most.
For more information on complex aneurysm repair or to schedule a consultation, visit the contact page. Stay connected with CCVSA through social media for updates and health tips: